Blog

  • The Neurosurgeon Interview

    The Neurosurgeon Interview

    Most patients go to a neurosurgeon expecting an expert in their condition. However, while a doctor may be a brilliant surgeon, their knowledge of complex Ehlers-Danlos Syndromes (EDS) comorbidities can rank dangerously low.

    Traditional Chiari decompression has an estimated failure rate approaching 50%. When a surgeon claims a “100% success rate,” be highly cautious. They are usually measuring mechanical completion (the bone was removed, the patch was sewn in) rather than how the patient actually feels.

    Furthermore, data from our community of over 10,000 members reveals a deeply deceptive tactic used to protect these perfect statistics: these surgeons systematically cherry-pick their cases, dismissing complex patients before surgery—and entirely abandoning them if they develop a post-decompression problem afterward.

    When a hypermobile patient experiences a post-op slump, worsening fluid pressure, or progressive instability, these surgeons routinely gaslight them, claim the operation was a structural success, and tell them to find a new neurosurgeon when post-decompression problems appear. By erasing injured patients from their clinics, they erase them from their failure data.

    We deserve better than a tidy post-op scan followed by medical abandonment. Use the interview script below to find out if your surgeon understands a crowded skull versus a prolapsing brain.


    • Defining the Anatomy:
      How do you differentiate between a true congenital Chiari malformation and an Acquired Chiari Malformation driven by connective tissue laxity? Since the standard diagnostic criteria for Chiari is based entirely on the size of the tissue prolapse (herniated tonsils) rather than the physical size of the skull cavity, an MRI report for a congenital crowded skull and an Acquired prolapsing brain will look completely identical. How are you ruling out the latter before operating?
    • Volumetric Data:
      Are you basing my diagnosis solely on the millimeter drop of my cerebellar tonsils? Did my radiologist measure the physical volume of my posterior fossa to prove my skull cavity is actually too small?
    • The Prolapsing Risk:
      If my posterior fossa volume is normal, but my ligaments are fragile, how will performing a decompression prevent my hindbrain from simply prolapsing further into the newly enlarged opening?
    • The Chiari 1.5 Distinction:
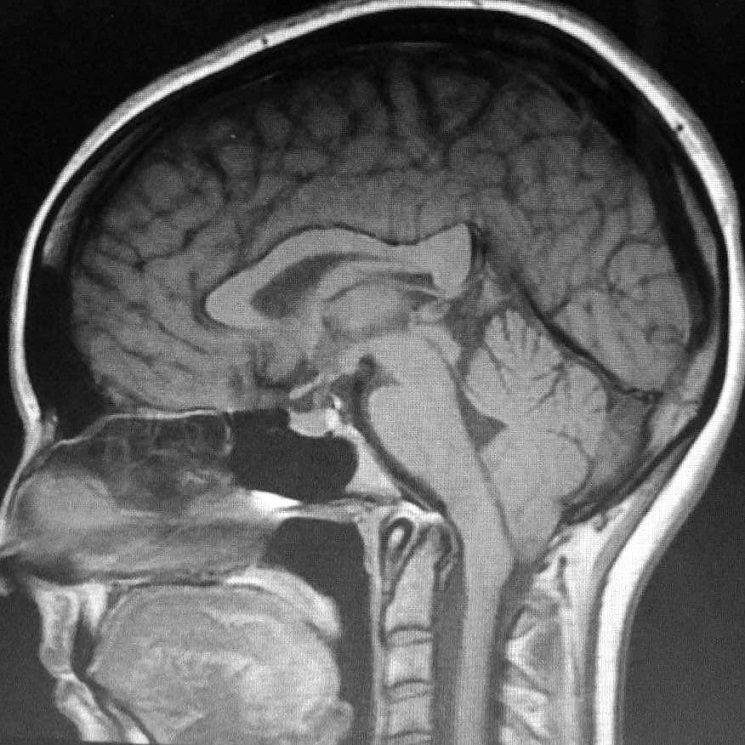
      Looking at my sagittal scans, is any part of my medulla oblongata (brainstem) herniated or elongated below the foramen magnum? If yes, how does a basic decompression address this altered brainstem position?

    • The Core Measurements:
      What are my exact measurements for the Clivo-Axial Angle (CXA), Grabb-Oakes, and Harris measurements? [1]
    • Dynamic Imaging:
      Since instability is a motion failure, will you order Upright Dynamic (Flexion/Extension) MRI or Digital Motion X-Ray (DMX) to calculate how many millimeters my skull translates when moving? [2]
    • The Subaxial Foundation (C3–C7):
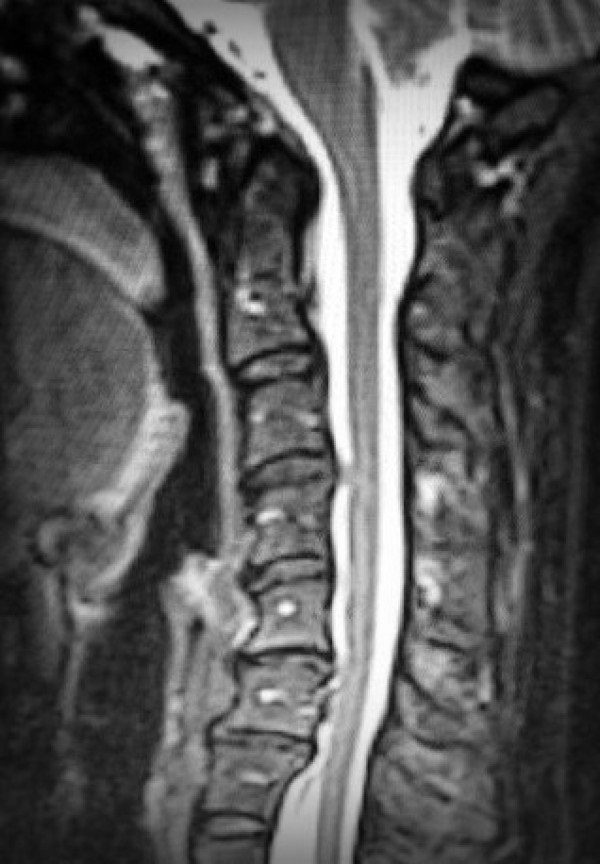
      Have you evaluated my mid-to-lower neck for Subaxial Instability (SAI) and premature Degenerative Disc Disease (DDD)? If my lower neck column is unstable or collapsing, how will my upper neck withstand the stress of a skull-base decompression? [4]
    • The Full-Spinal & Brain Scan Blindspot:
      If you are ordering a cervical scan but refusing a brain scan (or vice versa), how can we accurately map my neuro-anatomy? Since the central nervous system is one continuous column, how can we safely plan an irreversible surgery without a complete visualization of my brain down to my lumbar spine?
    • The Syrinx Origin:
      If I have a Syringomyelia (syrinx), how are we ruling out localized spinal cord compression from C3–C7 instability as the true driver of the cavity, rather than a skull-base blockage alone? If you refuse to scan my thoracic and lumbar spine, how can we be sure there isn’t a secondary syrinx or a tethering point fueling this fluid buildup? [4]

    • Addressing the Occult:
      Are you experienced in diagnosing Occult Tethered Cord Syndrome (OTCS)? If my conus medullaris terminates at a “normal” level on a standard supine MRI, how are we ruling out a tight, stretched cord that is anchoring my nervous system? [3]
    • Advanced High-Resolution Imaging:
      Will you order a CISS (Constructive Interference in Steady State) MRI sequence of my lumbar spine? Since standard thick-slice MRIs miss micro-structural tension, will we use a CISS sequence to check for a thickened filum terminale or nerve roots pinned against the spinal canal walls? [3]
    • Prone Imaging Dynamics:
      Will you order a Prone Lumbar MRI (lying on your stomach) alongside the CISS sequence to see if my spinal cord is pathologically anchored and fails to float forward normally? [4]
    • Medullary Stretching & Dysautonomia:
      Are my profound autonomic symptoms (POTS, blood pressure crashes) coming from direct brainstem compression, or is a tethered cord stretching my medulla oblongata from the bottom up? [3, 4]
    • Surgical Order of Operations:
      If I have an occult tethered cord pulling my brain down, why should we decompress my skull before releasing the bottom tension? Won’t the rubber-band pull simply drag my brainstem deeper into the empty surgical site?

    • The S.E.E.P.S. Scan Review:
      Do you see any of the classic signs of spontaneous intracranial hypotension (SIH) on my brain MRI? [5]
      • S — Subdural fluid collections?
      • E — Enhancement of the pachymeninges (brain lining)?
      • E — Engorgement of dural venous structures?
      • P — Pituitary hyperemia (enlargement)?
      • S — Sagging of the brain/brainstem?
    • The Invisible Fistula:
      Are you aware that CSF-Venous Fistulas (CVFs) act like an open drain, siphoning my brain downward, yet leave zero fluid pools on standard spinal MRIs? [5]
    • Advanced Imaging Verification:
      If I have a clear orthostatic (positional) headache but a “normal” MRI, will you refer me to a specialized CSF leak center for a Digital Subtraction Myelogram (DSM) or Ultrafast CT Myelogram to find the hidden fistula or leak before operating on my head? [6]

    • High-Pressure Structural Signs:
      Does my brain MRI show an Empty Sella (or partially empty sella), flattened lateral ventricles, or distension of the optic nerve sheaths? [7]
    • Venous Stenosis Assessment:
      Since dural sinus collapse is highly prevalent in the EDS population, will you order a Magnetic Resonance Venogram (MRV) to evaluate my internal brain drainage? [7]
    • The Outside-In “Eagle” Compression:
      Because I have a hypermobile neck, will you order a 3D-CT Reconstruction of my skull base to rule out Eagle Syndrome? Are my elongated or calcified styloid processes mechanically crushing my internal jugular veins when I turn my head? [7, 8]
    • The Post-Op Slump Risk:
      If my brain is being pushed down by high pressure from a blocked vein or Eagle Syndrome, how will a decompression fix my drainage? Won’t the high pressure simply shove my brain stem directly into the newly created space? [8]
    • Cranial Valve Check:
      If my high pressure has caused a Cranial CSF Leak (fluid leaking from nose or ears), why should we patch the leak before clearing the venous blockage that caused the pressure to blow out in the first place?

    If a neurosurgeon answers defensively, dismisses your measurements, or attempts to schedule an immediate decompression while ignoring met diagnostic criteria in Track 1, 2, 3, or 4: STOP.

    An untreated comorbidity is the primary driver of a failed surgery. Walk away, protect your anatomy, and find a surgeon who treats the human being, not just the herniation.

    You are informed, empowered, and absolutely Worth the Fight (WTF!)

  • Understanding “Neuro-EDS”: A New Way to Look at Complex Symptoms

    A landmark medical paper has proposed a new clinical category called Neuro-EDS. This concept should help doctors better recognize and treat patients with severe, overlapping neurological issues alongside joint hypermobility. [1, 2]

    It is a phenotype, not a new genetic subtype. Neuro-EDS describes a specific pattern of symptoms that cluster together in a subgroup of hEDS/HSD patients. [1]

    • It validates complex cases. It connects the dots for patients who suffer from severe spinal, neurological, and autonomic issues that are often dismissed by standard doctors. [1]
    • It aims for future precision medicine. Researchers hope this clinical description will eventually help identify the specific biological and genetic causes (the “endotype”) behind these symptoms. [1]

    The medical paper organizes Neuro-EDS into two highly interconnected symptom categories: [1]

    1. The Cranial and Spinal Domain

    This domain covers structural and mechanical problems where the skull meets the spine, often caused by loose, fragile ligaments. [1]

    • Craniocervical Instability (CCI): Excessively loose ligaments that fail to support the skull, leading to brainstem compression.
    • Atlantoaxial Instability (AAI): Instability between the first two vertebrae of the neck.
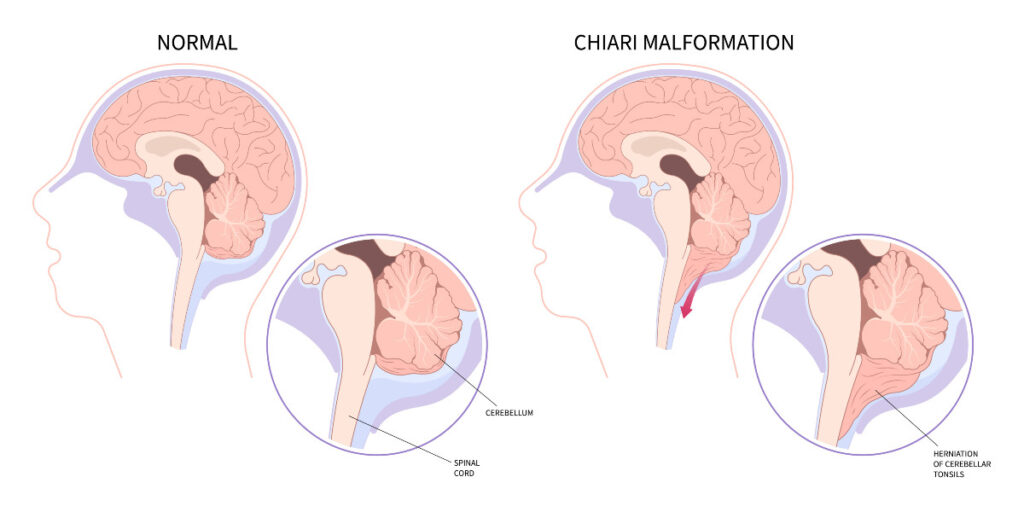
    • Chiari Malformation: The lower part of the brain slipping down into the spinal canal.
    • Tethered Cord Syndrome: The spinal cord being abnormally pulled or attached to the spinal column.
    • Positional changes: Symptoms that worsen significantly when standing, moving, or changing head positions, which often require upright or movement-based (dynamic) imaging to properly catch. [1, 2]

    2. The Neuro-Autonomic-Inflammatory Domain

    This domain covers the systemic, functional, and chemical issues that frequently co-occur with structural spinal problems. [1]

    • Dysautonomia / POTS: Malfunctioning of the autonomic nervous system, causing severe dizziness, heart rate spikes, and poor blood flow to the brain upon standing. [1]
    • Mast Cell Activation Syndrome (MCAS): An overactive immune response where cells inappropriately release inflammatory chemicals, triggering full-body allergic reactions, pain, and brain fog. [1]
    • Neuropathic Pain: Chronic nerve pain, often driven by small fiber neuropathy or systemic neuroinflammation. [1, 2]

    Reducing Psychiatric Misdiagnosis
    Many patients with these complex symptoms are told their physical issues are “just anxiety” or psychosomatic. Formally naming this clinical pattern helps protect patients from inappropriate psychiatric labeling. [1]

    Improving Coordinated Care
    Because Neuro-EDS links the nervous system, spine, and immune system, it provides a blueprint for a multidisciplinary care team. It encourages neurosurgeons, neurologists, immunologists, and physical therapists to collaborate rather than working in isolated silos. [1, 2]

    Unlocking Target Research
    Grouping these patients together lets scientists build registries and run targeted genetic trials. This is the necessary first step to finding a cure and creating personalized, highly effective treatments. [1]


    For More About Neuro-EDS:

    • Watch the following video recently released:

    “Postquam visibile, numquam neglectum” is a Latin motto that translates to “Once recognized, never overlooked.”

    ~Center for Neuro-EDS

    1. Bloom AR, Ruhoy IS, Dass RA, Lerner A, Bolognese PB, Klinge PM. Defining Neuro-EDS: A Neuro-Predominant Phenotype in hEDS/HSD and Related Heritable Connective Tissue Disorders. Preprints. 2026 Aug. doi: 10.20944/preprints202608.0567.v1. Available at Preprints.org Portal.

    2. Henderson FC Sr, Austin C, Benzel E, Bolognese P, Ellenbogen R, Francomano CA, Ireton C, Klinge P, Koby M, Long D, Patel S, Singman EL, Voermans NC. Neurological and spinal manifestations of the Ehlers-Danlos syndromes. Am J Med Genet C Semin Med Genet. 2017 Mar;175(1):195-211. doi: 10.1002/ajmg.c.31549. Epub 2017 Feb 21. PMID: 28220607. Available at PubMed.

  • You, the Advocate: Getting Started With Self-Advocacy

    You, the Advocate: Getting Started With Self-Advocacy


    This mindset influences your actions and shapes how others perceive, believe in, and respond to you. It also determines the extent to which your medical team and support systems can assist you. Others can only support us as much as we value ourselves and are willing to invest in our own well-being. Your self-image and self-appreciation directly impact your ability to advocate for yourself and assert your rights as a deserving individual and patient. You have the right to take the time to express your concerns and ask questions, with the expectation of being listened to, supported, and respected without bias. Furthermore, you are entitled to all information about your health so you can make informed decisions about your care and livelihood. Unfortunately, we do not always receive this from medical professionals or government agencies, despite years of contributing to these systems. Therefore, it is essential to be prepared to advocate for yourself when necessary.

    EMPOWER YOURSELF THROUGH EDUCATION

    Learn and understand your diagnosis. Researching and understanding a Chiari diagnosis is crucial for self-advocacy; learning to utilize online resources, articles, and support groups to gather information. Finding reputable, evidence-based sources, such as those referencing peer-reviewed studies, helps justify concerns to medical professionals despite encountering conflicting information due to ongoing, rapid research in the field. For more information, visit Chiari Bridges.

    Learn and understand your diagnosis. Researching and understanding a Chiari diagnosis is crucial for self-advocacy, which includes learning to utilize online resources, articles, and support groups to gather information. Most of the information available is found online in articles, websites, videos, and online support groups. Finding accurate, up-to-date, and reputable sources is paramount. Here at Chiari Bridges, we try to reference the studies and peer-reviewed articles behind our information, so you know the official sources that the information came from and will be better able to justify your requests and concerns to your doctors. Regardless of your source, be prepared to find a lot of conflicting information. These contradictions mainly exist because Chiari and its co-morbid conditions are being researched like never before, so it’s an exciting time, but that fails to give much comfort to those having to fight with their doctors on the existence of every symptom they face.

    Know your rights as a patient and your doctor’s legal responsibilities. Rights and responsibilities are often governed by state and federal laws and are outlined and included in the paperwork given to you from medical practices, health care systems, hospitals, and facilities. Your providers will likely require you to sign that you agree to and understand them. In doing so, these are legally binding for both parties. Thus, you will want to make sure you understand them fully before signing them and get a copy for your own records (if they don’t give them to you, don’t be afraid to ask for a copy).

    Learn and understand your health insurance. Know what your policy does and does not cover. Become familiar with which doctors, medical services, and facilities are covered. Find out about copays, deductibles, out-of-pocket costs, and other relevant information. Find out if your policy includes out-of-network benefits and associated costs, including out-of-state benefits. If no out-of-network/out-of-state benefits exist, find out if exceptions can be made. Almost all insurance plans do have some form of exceptions and/or appeals process for this very purpose. There are commonly two stages of appeal: an internal review (your appeal is reviewed in-house) and an external review (where you are specifically asking for a review made by an outside organization that has not been a part of your provision of care and has no conflict of interest).

    Learn about Advance Directives, Living Wills, Durable Healthcare Power of Attorneys, etc. You will want to familiarize yourself with all of these and decide what, if any, is right for you.


    EMPOWER YOURSELF BY DEVELOPING SKILLS AND ACCESSING TOOLS

    Communication Skills and Tools. Learning to know when and how to communicate your needs and desires to others is important, especially when you have a limited amount of time with your doctor. Brevity, clarity, relevance, problem-solving, negotiating, and preparation are key skills and tools. It might be beneficial to sit down beforehand and write the specific points you want to address and your ultimate goal for the appointment. Maintaining a respectful dialogue is always of utmost importance. Keeping your emotions under control is crucial.  Otherwise, your doctor might take you less seriously or assume your symptoms stem from psychological causes.

    Medical Records. As a patient, it is important to always obtain a copy of your medical records and review them for accuracy. It was once thought amongst medical professionals that a patient’s medical records were solely for doctors to communicate amongst themselves. Some medical professionals still hold to this antiquated ideology and become obviously disgruntled that you have chosen to exercise your patient right to not only obtaining your medical records but also, demanding they are 100% accurate. What is listed in those medical records will be used to treat you. It is important they are accurate and are corrected if they are not.

    Keep copies of all imaging and radiology reports. Images are not kept forever, nor are other medical records. Sometimes doctors do not tell you some of the things found in your imaging/reports and other tests because they deem them “incidental” or irrelevant. Sometimes, doctors miss what is obviously clear altogether. Many Chiarians go through years of misdiagnosis before being properly diagnosed. Often, a look back through your medical records will show patterns and assist in the discovery, diagnosis, and treatment.

    Patient Portals. With the advent of portals being used in many practices and facilities, patients now have easier, free access to many of their medical records. The same rules apply to the information retained in the portals regarding how long it is kept there. Any conversations you might have with your provider through the portals should be saved as well.

    Organization and Preparation. Every person has their own way of “organizing.” This extends to your medical records keeping as well as preparation for appointments. There are some free online resources to help you with this organization. Some like to make a “chart” for their medical records by creating a binder with tabs. Some use digital charts/record-keeping tools for free online or for purchase. Many phone apps exist to help as well. However you decide to organize is up to you, but it is an invaluable tool to help you arm and equip yourself for self-advocacy.

    Self-Care and Coping Skills. We often underestimate the necessity of self-care, as well as the power of developing positive, healthy coping skills and techniques. Self-care is pretty standard for all: getting proper nutrition, rest, appropriate and safe exercise, taking meds faithfully, taking time for recreation and refreshment, and tending to the beauty that is your body, mind, and spirit. Everyone has ways they “cope” in life in general and within the framework of chronic illness. It’s important to find the ones that work for you.


    EMPOWER YOURSELF BY FINDING THE RIGHT DOCTOR(S)

    Self-Education. Self-education precedes the ability to find a good doctor. If you are not aware and knowledgeable about your diagnoses and disorders, you will not recognize whether a doctor is the right one for you. Educate yourself on your conditions and on what your potential doctor has published on your conditions: What are their credentials, experience, affiliations, number of cases they have treated, and specialties and sub-specialties? Look for any official publications, scientific journals, or other research that your provider may have written. Additional information can be found online through state records and other sources regarding your physician.

    Ask family, friends, and other medical professionals. Find others who have PERSONAL FIRST-HAND doctor/patient experience with the potential provider. Keep in mind a doctor can be a great fit for one patient but not for another. You can also ask for the opinion of your present doctors or other medical professionals.

    Getting 2nd Opinions and When to Find Another Doctor. It is never wrong, always wise, and completely within your rights as a patient to seek a second opinion (or more). If you are facing a potential surgery or procedure that could be risky and/or permanent, it is prudent to get multiple opinions. It is your right to ask for and change doctors at any time or facility. You do not need to give any reason nor explain yourself, though you will likely be asked to do so. Be careful not to burn bridges or become “blacklisted.” Always find a new doctor before leaving the old one.


    EMPOWER YOURSELF BY DEVELOPING YOUR SUPPORT SYSTEM AND GETTING HELP. Being a self-advocate does not mean “going it alone.” Developing and surrounding yourself with a support system is vitally important, and many consider it to be “their lifeline” to keep going.

    Local or online support groups. Finding the right local or online group can be just as important as finding the right doctor and educating yourself. Remember, there is a lot of accurate and inaccurate info out there (even amongst our medical professionals). A support group is only as good as the respect they have for you in your fight. If they respect the Chiari fight, it will be evident in the way they treat one another and in the accuracy of the information they espouse and share. Online groups each tend to have a different set of rules that members are expected to follow: some allow and encourage advice and recommendations amongst their members, and some do not allow it at all. Not every group will be the right fit for each Chiarian, but you can expect any good group to be kind, supportive, respectful, accurate in the information disseminated, gentle in correcting inaccurate information shared, respectful of your autonomy and choices, and zero-tolerance for bullying.

    Workplace Support. There are laws that protect you, and that can even provide assistance and support within the workplace that you should familiarize yourself with. The Family and Medical Leave Act of 1993 (FMLA) is a federal law in the United States requiring employers to provide employees with up to 12 weeks of job-protected, unpaid leave for qualified medical and family reasons annually; but you must file it as FMLA leave to get the protection.

    School Support. There are programs and opportunities within schools that you should also familiarize yourself with and use to protect yourself if your Chiarian is in school. In the United States, the US Department of Education has worked hard to incorporate federal laws to help reduce discrimination and increase structured programs to help ensure the success of students with disabilities. As a result, most schools, including colleges, have programs where students with disabilities can get special allowances for recording devices, note takers, removal of time limits on tests, etc. These programs are usually subsidized at a state level and have different names depending on your state, but a school counselor should be able to point you in the right direction. These protections may be limited in privately funded colleges and universities that do not receive any public funds.

    Support and Assistance Programs. There are many programs, assistance, and support available in nearly every local area (through county trustees, charitable organizations, and churches), as well as state and federal programs. Just are few examples of help available are assistance with mortgage, rent, utilities, food, clothing, medical bills, medical insurance, free or reduced-cost prescriptions, holiday assistance, back-to-school, free or reduced-cost dental clinics, pro-bono legal help, cash assistance programs, etc.

    Professional Advocate Support. While self-advocacy is important, you might find that you need more help than you can accomplish alone. Managing your health can be confusing and overwhelming. Sometimes it can be hard to get your voice heard by the healthcare professionals around you. The healthcare system itself is very complicated. If you are having difficulty finding your way through the complex maze of healthcare, you might want to consider seeking the help of a professional advocate. There are hospital advocates, non-profit patient advocates, for-profit (employer-based) advocates, and independent advocates for you to turn to.

    Family and Friends Support. Chronic illness can take a huge toll on relationships. We all want and need the love and support of our family and friends. Not everyone has this support, making it all the more painful. No two families or friendships are alike. If you find a lack of support amongst your friends and family members, seek to restore it and, in the meantime, find another means of support, as Chiari is not something you want to fight alone. Support groups are a good alternative means to help find the support you need.

    Counseling Support. Sometimes we all find ourselves struggling to cope. Maybe we lack support or want to protect our relationships by not always talking about our problems to friends and family, yet need an outlet. Finding a therapist can be one of the best things we can do for ourselves. Doing so doesn’t mean you’re crazy or weak. It is a sign of strength and indicates that you value and respect yourself in every facet of your life, which brings us back to the reason we learn to self-advocate in the first place. Believe you are worth it – all of your body, mind, and spirit! If you ever find yourself in a life-threatening crisis, don’t be ashamed to contact a crisis hotline.

    When to get a lawyer. If you believe you are the victim of abuse, harm, malpractice, or neglect, consider speaking with a malpractice attorney. If you think your workplace rights are at risk, contact an employment lawyer. If you can no longer work due to your condition, look for a disability lawyer. Elder law attorneys may also be helpful, and their services are not limited to the elderly. Whenever you feel your rights have been violated, it may be time to seek legal counsel.

    Self-advocacy will empower you to know and speak up for yourself, make your own decisions, learn and exercise your rights and responsibilities, learn about your condition(s), and how to get accurate up-to-date information in order to make decisions concerning your care, treatment, and overall well-being. It will help you find the right doctors, support systems, options, resources, and get other help available to you. As you journey along in self-advocacy, you will grow both as a patient and a person. You will also discover many additional ways that self-advocacy benefits and empowers you, and in turn, you’ll be able to help pass those benefits on to others as well.


  • Recipe: Spiced Dandelion Root Tea Mix

    Recipe: Spiced Dandelion Root Tea Mix


    As with everything on our site, we encourage you to check with a doctor that understands nutrition before making this or anything a regular part of your diet.

  • Understanding Your Head and Neck Pain

    Understanding Your Head and Neck Pain

    Chiari headaches are felt at the occiput – at the base of the back of the skull and upper neck. They are generally tussive in nature, where they are exacerbated by valsalva maneuvers, which generally include: coughing, sneezing, heaving, laughing hard, or bearing down (like with a bowel movement or childbirth). These maneuvers reduce cardiac output (the amount of blood coming from the heart with each heartbeat), which in turn affects the attempted flow of cerebrospinal fluid, and it increases vagal stimuli. These headaches are often accompanied with feelings of vertigo, proprioception problems, gait problems, trouble swallowing, muscle spasms (commonly starts in the eyelids – blepharospasm), memory deficits, and cognitive difficulties (usually word recollection problems).

    Occipital headaches occur at the back of the lower skull (occiput) and upper neck, on one or both sides of the upper spinal cord.

    Pressure headaches are generally differentiated by position.

    • Low-pressure headaches: pressure is generally worse when upright and relieved by laying down.
    • High-pressure headaches: pressure is generally worse when laying down and relieved by being upright.
    • EXCEPTION TO THE RULE: Internal Jugular Venous Compression Syndrome (JVCS) increases intracranial pressure, but because the jugular vein is usually more open when laying down, it is usually relieved by laying down (which often causes confusion with low-pressure symptoms).

    Those that suffer from low-pressure headaches tend to report feeling like there is an invisible pressure pushing down from the top of the head, often making it feel like your “head is going to implode.” Low-pressure headaches are characterized by being worse when upright and relieved by laying down. Low-pressure headaches are typically a sign of a cerebrospinal fluid leak (CSF Leak). The longer that the leak has existed, the less obvious the positional element – meaning the patient can be upright longer before they feel the pressure at the top of their head and they tend to need to lay down longer before getting any measure of relief. Caffeine often helps relieve low-pressure headaches.

    Click image to view a more complete list of common low-pressure symptoms.


    High-Pressure Headaches (IH/IIH)

    Those that suffer from high pressure tend to feel pressure behind the eyes (often mistaken for sinus headaches) and report feeling like their “head is going to explode” from the pressure. High-pressure headaches are generally characterized by being worse when laying down – often awaking in the middle of the night or first thing in the morning with a headache, and the headache tends to dissipate to some degree after being upright for a period of time (and that period of time is different for everybody). Caffeine generally exacerbates high-pressure headaches.

    Click image to view a more complete list of common high-pressure symptoms.


    Connecting the Three Headaches

    All of these are most common in patients with a connective tissue disorder such as Ehlers-Danlos Syndrome.

    • Untreated high pressure can push the cerebellar tonsils down into the foramen magnum where it blocks the flow of cerebrospinal fluid, leading to an Acquired Chiari Malformation (usually simply diagnosed and treated as a Chiari 1 Malformation) AND the blockage of cerebrospinal fluid further increases intracranial pressure.
    • Untreated high pressure can cause cranial leaks – often accompanied by cerebrospinal fluid leaking through the nose (CSF Rhinorrhea) or less commonly, the ears. (This can temporarily reduce intracranial pressure and its symptoms.)
    • Cranial leaks (often misdiagnosed with allergies) can sometimes seal on their own as the pressure reduces, leading to rebound high pressure (which is temporary) or continued high pressure if they originally had high pressure.
    • Untreated spinal leaks can create a suctioning or pulling down (sag) effect where the cerebellar tonsils get lodged into the foramen magnum, creating an Acquired Chiari Malformation (usually simply diagnosed and treated as a Chiari 1 Malformation). Once there, it blocks the flow of cerebrospinal fluid and increases the pressure (which can reduce spinal pressure and increase intracranial pressure), leading to the occipital headaches and other symptoms associated with any Chiari Malformation.

    Major Problem Regarding Our Diagnoses & Treatment Options:

    1. Doctors and radiologists alike, tend to see the herniated tonsils and assume a small posterior fossa.
    2. Most do not check for high-pressure or low-pressure, even when directly asked and symptoms are present.
    3. When a posterior fossa decompression is finally offered, the high or low pressure is often left untreated which leads to a failed decompression.
    4. By the time sufferers get a name to go with their symptoms, we jump at the opportunity for relief.

    The “Bobble-head Sensation” – When It Feels Like Your Neck Can No Longer Hold Up Your Head

    While most of us experience this feeling either intermittently or continuously, it is generally related to structural instability issues:

    • Craniocervical Instability (CCI, also known as Syndrome of Occipitoatlantialaxial Hypermobility) involves vertical hypermobility (back and forth sliding) of the craniocervical junction (interface between the occipital bone and the 1st and 2nd vertebrae), where the neck is no longer properly supporting the cranium. This condition can be dangerous as it often involves brain stem compression that can lead to a vast array of symptoms of Dysautonomia (dysfunction of the Autonomic Nervous System – ANS).
    • Subaxial Instability (SAI; also known as Cervical Instability) involves hypermobility of the C2/C3 to the C7 intervertebral discs. This condition (like most conditions involving the cervical spine) is a major cause of muscle spasms (in the neck and throughout the body at any point below the disc issues. When these neck spasms occur, they can cause the “Bobble-head sensation” where it feels like your neck can no longer hold up your head. This disc degeneration can lead to paralysis as discs compress the spinal cord.

    Important Questions to Ask Your Neurosurgeons: https://chiaribridges.org/important-questions-for-your-neurosurgery-appointment/.


    Originally written 10/2019
    Updated 12/2022

    Updated 11/2024
    Updated 3/2026

  • New Chiari & Comorbid Symptoms Compilation

    New Chiari & Comorbid Symptoms Compilation


    These are more than just Chiari symptoms, but they are important, because we usually have more than just Chiari. This is a pretty thorough list. It can be a little emotional for some, as it has a lot of symptoms that doctors have dismissed.

    • Print out this PDF.
    • Go over the list and put a dot next to all of the symptoms that you have EVER experienced
    • Go back over the list and put a check mark next to all of the symptoms that you are CURRENTLY experiencing.
    • Go back over the list and highlight the ten symptoms that would help you get your life back the most, and start there!

    NEW LIST


    OLD LIST

Chiaribridges

FREE
VIEW